
To Buy Tetracycline Online Visit Our Pharmacy ↓
Risks of Antibiotic Exposure on Fetal Development A mother's medication choices can feel like a crossroads, where protecting her health must be weighed against fetal vulnerability. Certain antibiotics cross the placenta and, depending on timing and dose, may disrupt organogenesis or interfere with mineralization. Longer or repeated courses increase exposure risk, while animal studies and human cohorts offer varying degrees of evidence and uncertainty. Clinicians should balance maternal infection control with safer alternatives, clear counseling, and shared decision making to minimize potential harm, and follow-up monitoring when exposure occurs, and emphasize prevention measures including vaccination where appropriate. Tetracycline in Pregnancy: Safety and Alternatives
How Common Antibiotics Affect Infant Bones and Teeth
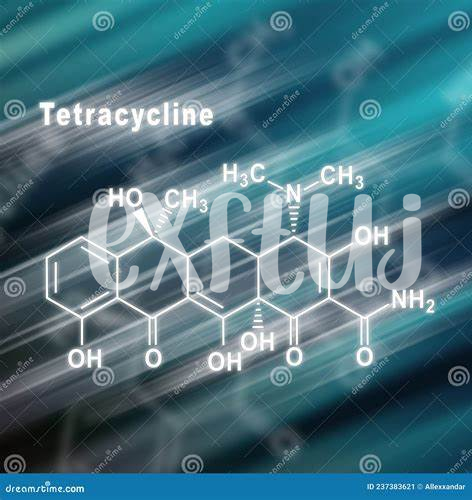
At a prenatal visit many women worry about drug effects. Several antibiotics cross the placenta and reach fetal circulation, where they may interfere with mineralization and cell growth in bones and teeth.
tetracycline classically chelates calcium, staining deciduous teeth and reducing enamel formation if exposure occurs during odontogenesis. Other agents can alter bone remodeling or reduce birth mineral stores.
Timing determines the risk: first-trimester organogenesis and second-trimester hard tissue development are especially vulnerable. Even transient exposure can have lasting cosmetic or functional consequences.
Clinicians balance infection control with fetal safety by choosing alternatives, minimizing duration, and counseling mothers about specific risks and follow-up dental assessment after birth and arranging pediatric dental and skeletal follow-up visits.
Timing Matters: Exposure Windows Across Pregnancy Trimesters
Pregnancy unfolds in distinct windows: early embryogenesis in the first trimester shapes organ systems and carries the highest risk for structural malformations, while later trimesters focus on growth and tissue maturation. Antibiotic exposure during each phase can have different consequences, so clinicians weigh timing alongside infection severity.
Specific agents matter: tetracycline is avoided because deposition in fetal bone and teeth occurs mainly in the second and third trimesters. When antibiotics are necessary, choose safer alternatives and schedule treatment to minimize fetal harm, counseling patients about trimester‑specific risks and benefits carefully.
Balancing Maternal Infection Control with Fetal Safety
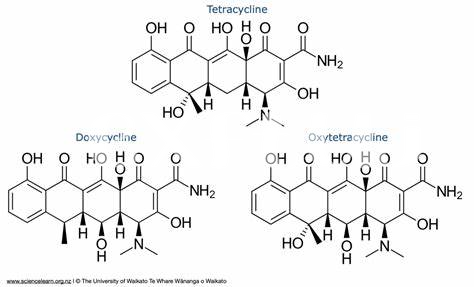
Facing infection during pregnancy can feel like a tightrope walk; mothers and clinicians weigh immediate maternal health against long-term fetal outcomes. Antibiotics such as tetracycline carry known risks, prompting careful risk–benefit discussions and tailored choices.
Timing of therapy matters: first trimester exposures may threaten organogenesis, while later treatment affects growth and mineralization. Shared decision-making should consider infection severity, gestational age, and available alternatives to protect both patient and fetus safely.
Where possible, use narrower-spectrum agents with established pregnancy safety profiles. Avoid tetracycline class drugs when alternatives exist. Close monitoring, dose adjustments, and consultation with obstetrics, infectious disease, or clinical pharmacology help optimize outcomes and follow-up.
Explain risks and benefits clearly, acknowledging uncertainty while offering concrete plans: labs, symptom checks, and contingency steps. Empowered patients engage in safer care, improving adherence and ensuring infections are treated promptly without unnecessary fetal exposure.
Recommended Safer Antibiotic Alternatives during Pregnancy
When infection threatens pregnancy, clinicians weigh maternal benefit against fetal risk. Many first-line agents are safe; awareness avoids outdated choices like tetracycline, which is usually avoided due to dental and bone effects.
Beta-lactams such as penicillins and cephalosporins treat most common infections and have long safety records in pregnancy. Macrolides are alternatives when beta-lactams are unsuitable.
For certain resistant infections, targeted therapy guided by culture and susceptibility spares broad-spectrum exposure. Collaboration with obstetrics and infectious disease specialists ensures optimal maternal outcomes with fetal protection.
| Antibiotic | Use |
|---|---|
| Amoxicillin | Common safe |
| Cefazolin | Surgical prophylaxis |
| Azithromycin | Alternative for allergy |
| Nitrofurantoin | Urinary infections in pregnancy caution |
| Clindamycin | Skin and pelvic infections |
| Consult specialist for resistant cases and culture-guided therapy | |
Practical Prescribing Tips and Patient Counseling Strategies
Begin with a careful risk–benefit assessment, confirming the infection warrants antibiotics and documenting diagnostic evidence. Review allergy history, current medications, and gestational age to guide safe choices.
Prefer agents with established pregnancy safety profiles, adjust doses for physiological changes, and avoid known teratogens unless no alternatives exist. Coordinate with obstetrics when infections could affect fetal outcomes.
Explain expected benefits, possible fetal risks, and common side effects in plain language. Encourage questions, provide printed instructions, and emphasize adherence and prompt reporting of fever, rash, or unusual bleeding.
Arrange follow-up to reassess infection response and fetal well‑being, advise avoiding over‑the‑counter tetracyclines, document counseling clearly, and provide urgent contact information for concerns and arrange pediatric notification when appropriate.